World Stroke Day 2026: All About AVMs And Brain Haemorrhage

Brain arteriovenous malformations (AVMs) are developmental abnormalities in which arteries connect directly to veins, bypassing the normal network of tiny blood vessels called capillaries that supply oxygen and nutrients to brain tissue. This tangle of abnormal vessels, known as the nidus, can remain undetected for years but may sometimes rupture, causing a potentially life-threatening brain haemorrhage.
What Are The Symptoms?
Warning signs include a sudden, severe headache, seizures, loss of consciousness or new neurological problems, all of which require immediate medical attention. Some AVMs may also cause vision disturbances or tinnitus, while others are discovered incidentally.
“Brain AVMs may initially start small in infancy and early childhood and grow with the child’s development, as well as due to the abnormally high blood flow within the AVM,” said Dr. Chinmay Nagesh, Senior Consultant in Stroke and Neurovascular Intervention and Endovascular Interventional Radiology at Apollo Speciality Hospital, Bengaluru.
Accurate imaging and timely specialist evaluation help doctors assess the AVM and decide whether treatment is needed and which approach is most suitable, including embolisation in selected cases. As not every AVM requires the same approach, management must be individualised, balancing the risks posed by the malformation against those of intervention. Regular follow-up helps doctors monitor the patient’s condition and check the treatment results.
What To Do When An AVM Ruptures
“When an AVM ruptures and causes a brain haemorrhage, the immediate priority is to stabilise the patient,” said Dr Vikram Huded, President of the Indian Stroke Association; Senior Consultant, Director and Clinical Lead of the Interventional Neurology Programme at Narayana Health Group; Governing Council Lead of Neuroscience; and Head of Neurology, Bengaluru.
Treatment may involve securing the airway and circulation, controlling blood pressure and preventing further brain injury. Doctors also manage complications such as raised pressure inside the skull, seizures and hydrocephalus, a build-up of fluid in the brain. Some patients may require emergency surgery or other procedures to relieve pressure or control bleeding. Urgent evaluation by a multidisciplinary team of stroke specialists, neurosurgeons and neurointerventional specialists is essential.
Why Are Some Brain AVMs Difficult To Treat?
Brain AVMs vary in complexity. Those located deep within the brain or near areas controlling speech, movement or vision are particularly challenging because treatment-related injury can cause significant disability. Dr. Chinmay said large or diffused AVMs, those supplied by multiple small or tortuous arteries, and those with complex deep venous drainage may be difficult to treat safely through embolisation alone. Associated aneurysms and fragile blood vessels can further complicate treatment.
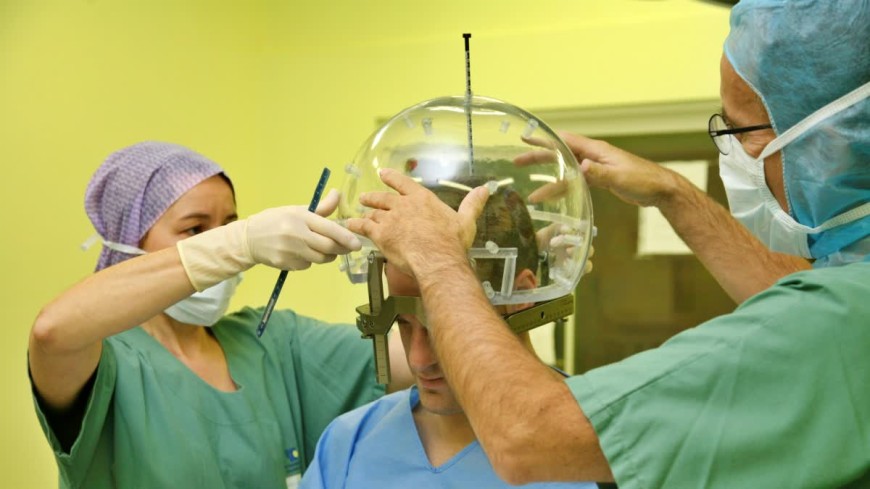
Experts say treatment choice depends on the AVM's size, location, and structure; the patient's age and overall health; history of haemorrhage; and the risks associated with each treatment option. Dr. Chinmay and Dr Huded explain that microsurgery can immediately remove an AVM if it is surgically accessible. Endovascular embolisation uses a catheter to block abnormal vessels and may be performed alone or in combination with surgery or radiosurgery. Embolisation alone may be suitable when complete and safe closure is achievable. Stereotactic radiosurgery uses focused radiation to close abnormal vessels gradually and may be considered for smaller AVMs or those in difficult-to-reach locations. As this process takes time, the risk of haemorrhage may persist until the AVM is completely obliterated. Some patients may be monitored if the risks of intervention outweigh the potential benefits.
Dr. Chinmay added that complex AVMs may require a combination of embolisation, microsurgery and radiosurgery. A multidisciplinary team of interventional neuroradiologists, vascular neurosurgeons and radiosurgery specialists should decide the best approach, prioritising the patient’s long-term neurological function.
What Is Endovascular Embolisation?
Endovascular embolisation is a minimally invasive procedure that does not require open surgery or a craniotomy. Dr. Chinmay noted that tiny microcatheters, as small as 0.3 mm in diameter, are guided through blood vessels into the AVM’s feeding arteries under real-time X-ray guidance. A biocompatible medical glue is then injected to block abnormal vessels within the nidus.
Not all AVMs require treatment. Many unruptured AVMs that cause zero or mild symptoms may be monitored regularly after discussing the risks and benefits with the patient and family. Embolisation may be considered for a ruptured AVM or one causing significant symptoms or neurological problems. Patient selection depends on the AVM’s location and angioarchitecture. The procedure may be performed in one or more sessions, with the aim of curing the AVM, preparing it for surgery, complementing radiosurgery or providing palliative relief.
Embolisation can be challenging in large AVMs or those sharing blood vessels with healthy brain tissue. The main risks are bleeding and stroke, which can vary in severity. Careful assessment of blood vessels and blood-flow patterns, including with the microcatheter in place, helps minimise the risk of damage to healthy brain tissue. Given its complexity, the procedure should be performed by experienced neurointerventionalists at specialised centres.
When Is An AVM Considered Cured?
An AVM is considered successfully treated when imaging confirms that the abnormal connections between arteries and veins have been completely eliminated. Improvement in symptoms alone does not establish a cure. Dr. Huded emphasised that follow-up imaging, often using catheter-based digital subtraction angiography (DSA), is essential to confirm complete obliteration.
Dr. Chinmay explained that a ruptured AVM carries a significantly higher risk of rebleeding than an unruptured one. He estimated that, if left untreated, the cumulative risk may reach around 10% at one year, 25% at three years, 37.5% at five years and 50% at 10 years. In comparison, unruptured AVMs carry an annual bleeding risk of about 1-3%.
A partially treated AVM may continue to carry a substantial rebleeding risk, potentially comparable to or higher than that of an untreated AVM. According to Dr. Chinmay, this may occur because blood flow becomes concentrated in the remaining nidus, potentially increasing pressure within the abnormal vessels. Treatment therefore generally aims for complete obliteration. Once complete obliteration is confirmed, the risk of bleeding falls dramatically. He stressed that follow-up is essential after embolisation. DSA is usually performed within a few months to a year to confirm the treatment outcome. This may be followed by MRI or MR angiography (MRA) annually or every few years. If follow-up imaging raises suspicion of AVM recurrence, another DSA may be required to confirm it.
Recovery depends on the extent and location of the bleed, the patient's neurological condition, associated complications and the AVM's size and anatomy. Once the patient is stable, the team determines the most appropriate treatment to address the AVM and reduce the risk of another haemorrhage. Early intervention is crucial to improving outcomes, he added.
Advances In AVM Treatment
Dr. Chinmay said that cerebral DSA remains the gold standard for assessing brain AVMs. This minimally invasive day-care procedure involves guiding a catheter from the wrist or groin into the blood vessels supplying the brain. It helps doctors map the AVM's vascular architecture, including its feeding arteries, nidus size, blood-flow patterns and draining veins, while identifying associated weak points such as nidal aneurysms. Colour-coded flow maps can reveal areas of unusually slow or fast flow that may warrant closer assessment. Doctors use these findings, along with the AVM’s location, the patient’s age and clinical characteristics, to calculate risk scores and estimate the likelihood of complications over the next 5-15 years. Non-invasive imaging techniques, including 4D CT and MR angiography, can also help monitor changes in blood-flow patterns during follow-up.
Dr. Huded said advances in neuroimaging have helped doctors assess AVMs and plan treatment more precisely. Improvements in imaging, DSA, microcatheters, embolic agents and navigation systems have expanded treatment options, while better microsurgical planning, intraoperative imaging and neurophysiological monitoring help teams manage risks and protect critical neurological functions. Computational blood-flow modelling and AI-assisted imaging are being explored to support AVM assessment and treatment planning, although their clinical benefits require further validation.
Kumar Surender Sinwar, Founder and CEO of mlHealth360, said, “AI-based tools can help analyse brain CT and MRI scans, flag suspicious findings, identify feeding vessels, measure vessel size and prioritise urgent cases. Screening may be considered in people with certain hereditary conditions or a history of brain haemorrhage, depending on clinical assessment. AI can support image analysis and triage, but cannot replace a clinician’s judgement. Doctors must still base their decisions on the scans, symptoms and the patient’s medical history.”
Managing brain AVMs requires careful assessment, as not every AVM needs immediate treatment. Doctors must weigh the risk of haemorrhage against the possible risks of treatment before deciding on the best course of action.